Is Revision Rhinoplasty Risky? What patients need to know.

While no one wants to undergo a revision rhinoplasty, the unfortunate reality is that nearly 1 out of 5 patients in the United States who undergo rhinoplasty are not happy with their results and choose to pursue a revision. While the reasons for such a high rate of revision rhinoplasty has been discussed in previous posts, in this article let’s discuss the risks of undergoing repeat surgery and ways to mitigate and minimize those risks.

First things first, how long should I wait before getting revision rhinoplasty?

One of the easiest ways to reduce the risk of complications with revision surgery is to allow the nose sufficient time to after the initial rhinoplasty surgery. Adequate healing time means the skin has regained most of its blood supply, lymphatic drainage and elasticity to handle the trauma of another surgery. Sufficient healing time also allows for scars and tissues to mature, to allow for a clearer picture of what actually needs to be corrected. For most patients, this means waiting at least 9-12 months after a nose job to pursue a revision surgery, although this will depend on specific surgical history, individual anatomy, and the current state of the nose.

Why Revision Rhinoplasty is More Complex Than Primary Surgery

Revision rhinoplasties are not created equal. Sometimes the initial rhinoplasty came very close to achieving the aesthetic and functional goals of the surgery, and only a small tweak or subtle adjustment needs to be made to create a flawless result. Other times, the original surgery destroys the structure of the nose, resulting in significantly reduced function and extremely unattractive aesthetics. This can happen from an over-zealous initial rhinoplasty, unfamiliarity with a patient’s specific anatomy, or a lack of adequate technical prowess to perform the proper operation from the initial surgeon. In these cases, revision rhinoplasty must often re-establish the framework of the nose while restoring function and beauty simultaneously. This kind of revision surgery presents a significant challenge since the natural cartilage has been altered and depleted, the blood supply compromised, and healing becomes slightly more unpredictable since scar tissue will respond differently from native tissue.

What Risks Are Higher Versus Primary Surgery?

When a revision rhinoplasty involves minor changes, the risks remain very similar to the original surgery given sufficient time has passed to allow adequate healing of the nose prior to revision. In more complex revision cases, the risk of infection, poor scarring or poor wound healing, asymmetries, prolonged swelling, and the risk of wanting/needing additional revision surgery becomes higher than a primary rhinoplasty. More serious risks including vascular compromise leading to skin necrosis may be possibilities, and should be discussed with your operating surgeon. Smoking, vaping, intranasal drug use and a history of multiple prior rhinoplasties may increase this risk.

What Reduces the Risk?

Surgeon experience. Revision rhinoplasty requires a specific skill set that goes beyond primary rhinoplasty. Surgeons who specialize in revision work are familiar with the anatomical variability these cases present and have the reconstructive toolkit — cartilage grafting such as rib grafting, structural support techniques — to address them. An experienced revision rhinoplasty surgeon will be able to rebuild the entire nose, and so will be comfortable reconstructing any structures damaged during a previous rhinoplasty.

Timing. Operating too soon after a primary rhinoplasty increases risk. Most surgeons recommend waiting a minimum of 12 months to allow swelling to fully resolve and tissues to stabilize before proceeding with revision surgery. This allows the blood supply and lymphatic drainage of the nose to return to a level that can handle the stress of another surgery while minimizing the risk of vascular compromise and prolonged swelling.

Realistic expectations. Understanding that revision rhinoplasty is a longer process than primary rhinoplasty — and that swelling can obscure final results for over a year — helps patients navigate recovery with appropriate patience.

Thorough pre-operative planning. Detailed imaging, honest assessment of available tissue and cartilage, and clear communication between patient and surgeon about goals, limitations, and risks are essential to a good outcome.

How long should I wait before getting revision rhinoplasty?

One of the easiest ways to reduce the risk of complications with revision surgery is to allow the nose sufficient time to after the initial rhinoplasty surgery. Adequate healing time means the skin has regained most of its blood supply, lymphatic drainage and elasticity to handle the trauma of another surgery. Sufficient healing time also allows for scars and tissues to mature, to allow for a clearer picture of what actually needs to be corrected. For most patients, this means waiting at least 9-12 months after a nose job to pursue a revision surgery, although this will depend on specific surgical history, individual anatomy, and the current state of the nose.

Why is revision rhinoplasty more complex than primary surgery?

Revision rhinoplasties are not created equal. Sometimes the initial rhinoplasty came very close to achieving the aesthetic and functional goals of the surgery, and only a small tweak or subtle adjustment needs to be made to create a flawless result. Other times, the original surgery destroys the structure of the nose, resulting in significantly reduced function and extremely unattractive aesthetics. This can happen from an over-zealous initial rhinoplasty, unfamiliarity with a patient’s specific anatomy, or a lack of adequate technical prowess to perform the proper operation from the initial surgeon. In these cases, revision rhinoplasty must often re-establish the framework of the nose while restoring function and beauty simultaneously. This kind of revision surgery presents a significant challenge since the natural cartilage has been altered and depleted, the blood supply compromised, and healing becomes slightly more unpredictable since scar tissue will respond differently than native tissue.

What risks are higher with revision rhinoplasty versus primary surgery?

When a revision rhinoplasty involves minor changes, the risks remain very similar to the original surgery given sufficient time has passed to allow adequate healing of the nose prior to revision. In more complex revision cases, the risk of infection, poor scarring or poor wound healing, asymmetries, prolonged swelling, and the risk of wanting/needing additional revision surgery becomes higher than a primary rhinoplasty. More serious risks including vascular compromise leading to skin necrosis may be possibilities, and should be discussed with your operating surgeon. Smoking, vaping, intranasal drug use and a history of multiple prior rhinoplasties may increase this risk.

What reduces the risk of revision rhinoplasty?

Four factors matter most: surgeon experience with the reconstructive toolkit revision cases require, timing — most surgeons recommend waiting a minimum of 12 months after the initial rhinoplasty to allow tissues to fully stabilize, realistic expectations about revision being a longer process than primary rhinoplasty, and thorough pre-operative planning including detailed imaging and honest assessment of available tissue and cartilage.


The Bottom Line

Revision rhinoplasty is more technically demanding than primary surgery — but in experienced hands, it is a safe and effective procedure that helps patients achieve the results their first surgery didn’t deliver. The key is approaching it with the right surgeon, the right timing, and the right expectations.


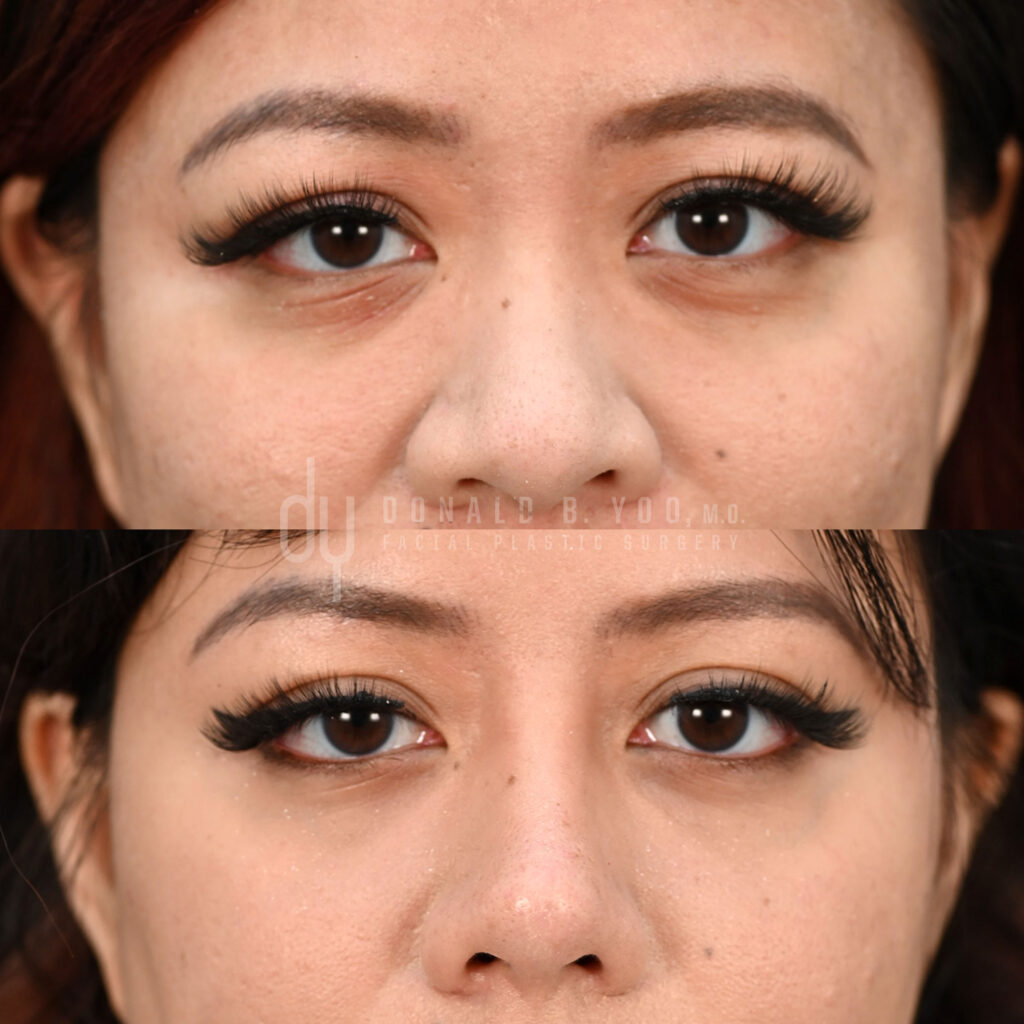
Before and after revision rhinoplasty with unified rib cartilage grafts and diced cartilage fascia to create a more refined and balanced nose.

Posted in Asian rhinoplasty, Revision rhinoplasty, rhinoplasty, septoplasty | Tagged , , , , , | Leave a comment

Revision Rhinoplasty After Botched Asian Rhinoplasty: What Went Wrong, and How To Fix It.

If you’re unhappy with the results of your rhinoplasty, you are not alone. According to studies, the revision rate after a primary rhinoplasty can reach 20% – meaning one out of five patients who undergo a nose job surgery will pursue a revision surgery at some point in their lives. Fortunately, for most patients, even with a botched rhinoplasty previously, the results can be corrected with revision surgery.

Asian rhinoplasty demands a different surgical approach than traditional rhinoplasty for both anatomical and aesthetic considerations. When a plastic surgeon does not adequately address the structural aspects of Asian anatomy, in addition to the effect of a thicker, more sebaceous skin envelope, the results often fail to meet the expectations of the patient.

Why Asian Rhinoplasty Requires a Different Approach

Softer, more pliable nasal tip cartilage, a lower dorsum (or nasal bridge) and thicker, more sebaceous skin compared to Caucasian anatomy means a different surgical approach must be taken. Common concerns for White patients undergoing rhinoplasty include a dorsal hump (bump along the bridge) or a wide, bulbous nasal tip. Nose job surgery remains relatively straightforward in these cases since since cartilage and bone can shaved or removed to reduce the hump and narrow the tip without too much concern that the structure of the nose will collapse. In addition, with relatively thin nasal skin envelopes, even small changes to the nasal framework will result in visible changes to the shape of the nose.

The Most Common Reasons for Failed Asian Rhinoplasty

  1. Incorrect selection of graft material
    • Using synthetic grafts always lead to complications at some point. Some patients are lucky and will not see any major issues for 20-30 years, but inevitably problems will arise that relate to implant migration, visibility, infection or even extrusion through the skin. Common synthetic implants include: silicone, Goretex, and Medpor.
  2. Inadequate structural support
    • For most Asian noses the cartilage shaping and supporting the tip of the nose is fairly weak and flexible. When the goal is to create definition and projection to the tip of the nose, this presents a less than ideal situation. If a rhinoplasty surgeon attempts to narrow the nasal tip in the same way he or she would narrow a White patient’s nose, the support of the nose weakens and is unable to show any definition through a relatively thicker skin envelope. In the worst botched rhinoplasty cases this will result in nasal valve collapse and an excessively pinched appearance to the nasal tip and ala, without any aesthetically pleasing “definition” added to the nose.
  3. Nostril and Tip Asymmetry
    • Many patients seeking Asian rhinoplasty also seek to have slimmer and more narrow ala and nostrils. In order to achieve this, a rhinoplasty surgeon must have mastery of structural grafting techniques (often requiring harvest of rib cartilage) and alarplasty (nostril narrowing) techniques to create a nose that maintains a completely natural shape, while also optimizing refinement. Surgeons unfamiliar with these techniques often end up with nostrils and nasal tips that have obvious asymmetry and even deviation.
  4. Unnatural Aesthetics
    • At the end of the day, the nose must be balanced with the rest of the face. As the central feature, it must enhance all the features around it and bring harmony to the face. A nose may look “fine” in isolation, but if the surgeon does not account for Asian aesthetics when shaping the nose, even a technically flawless operation can result in a botched nose.

What to Look for in a Revision Rhinoplasty Surgeon

If you’re considering revision surgery, look for:

  • Board certification in facial plastic surgery
  • Specific experience with revision cases, not just primary rhinoplasty
  • Before-and-after photos of revision patients, not only first-time surgeries
  • Experience with Asian and ethnic rhinoplasty specifically, given the anatomical differences discussed above

Final Thoughts

A disappointing rhinoplasty result can feel discouraging, but in most cases there is a path forward. Understanding why a result didn’t turn out as expected is the first step toward a successful revision.

Before and after revision Asian rhinoplasty
Before and After revision Asian rhinoplasty.

Posted in Asian rhinoplasty, Revision rhinoplasty, rhinoplasty | Tagged , , , , , , | Leave a comment

Why Smoking is Bad for Surgical Scars — And What You Can Do About It


Why Smoking is Bad for Surgical Scars — And What You Can Do About It

If you’re planning a surgical procedure, one of the most important things you can do to protect your results has nothing to do with choosing the right surgeon or following post-op instructions. It starts weeks before you even step into the operating room.

Smoking is one of the most significant — and most preventable — risk factors for poor surgical healing and visible scarring. Here’s the science behind why, and what you can do about it.


How Smoking Disrupts Wound Healing

Healthy scar formation depends on one thing above all else: adequate blood flow to the healing tissue. Smoking disrupts this process at multiple levels.

Nicotine causes vasoconstriction. Nicotine causes blood vessels to narrow, reducing circulation to the skin and underlying tissues. Oxygen-deprived tissue heals poorly — full stop.

Carbon monoxide displaces oxygen. Cigarette smoke contains carbon monoxide, which binds to hemoglobin more readily than oxygen does, further reducing the oxygen-carrying capacity of your blood.

Smoking impairs collagen synthesis. Collagen is the structural protein responsible for wound strength and scar remodeling. Nicotine directly inhibits fibroblasts — the cells that produce collagen — resulting in weaker, wider, and more visible scars.

Smoking suppresses immune function. A compromised immune response increases the risk of wound infection, one of the most common drivers of abnormal scarring and prolonged healing.

The cumulative result: smokers are significantly more likely to experience wound dehiscence (incisions reopening), delayed healing, infection, tissue necrosis, and thickened or widened scars compared to non-smokers.


Why Facial Surgery Is Particularly Vulnerable

In procedures like rhinoplasty and alarplasty, incisions are small and precise — often placed where skin is thin and blood supply is already limited. The margin for error is narrow. A wound that reopens or heals with excessive scarring in these locations is far more noticeable and far harder to correct than elsewhere on the body.


How Long Before Surgery Should You Stop?

Most surgeons recommend stopping smoking at least 6 weeks before surgery and abstaining for at least 6 weeks after. Eight or more weeks of cessation produces meaningfully better outcomes according to available evidence.

One important distinction: cutting back is not the same as stopping. Even reduced smoking continues to impair vascular function and oxygen delivery. Full cessation is the standard recommendation.


What About Nicotine Patches or Gum?

While nicotine replacement therapies (NRT) eliminate carbon monoxide and other combustion byproducts, nicotine itself — regardless of delivery method — still causes vasoconstriction. Patches, gum, and lozenges are useful quitting tools, but are not a surgical-safe substitute for smoking in the perioperative period. Discuss NRT timing with your surgeon and primary care physician well in advance of your procedure.


How to Mitigate Scarring Risk

Stop smoking as early as possible. Six weeks is the minimum; eight weeks or more is better. The longer you abstain, the more vascular function can recover.

Optimize nutrition. Protein, vitamin C, and zinc are essential for collagen synthesis. A nutrient-dense diet in the weeks surrounding surgery directly supports tissue repair.

Stay hydrated. Hydration supports circulation and tissue perfusion — both of which are already compromised in smokers.

Follow wound care instructions carefully. Keeping incisions clean, protected from UV exposure, and properly moisturized during early healing makes a meaningful difference in long-term scar quality.

Ask about scar management treatments. Silicone sheeting, scar massage, and in-office treatments such as laser resurfacing or microneedling — introduced at the appropriate healing stage — can significantly improve scar appearance over time.

Be honest with your surgeon. If you smoked close to your procedure date, your surgical team needs to know. This directly affects planning and post-operative monitoring.


Frequently Asked Questions

Can smokers get rhinoplasty or facial surgery? Yes — but with important caveats. Most surgeons will require a period of smoking cessation before proceeding, typically a minimum of six weeks. Patients who continue smoking up to the time of surgery face significantly higher risks of complications, poor healing, and visible scarring.

How long after surgery can I smoke again? Most surgeons recommend abstaining for at least six weeks post-operatively, as the critical phases of wound healing — including collagen remodeling — continue well beyond the first few days. Resuming smoking too early can compromise results even after a smooth initial recovery.

Does vaping or using e-cigarettes carry the same risks? Yes. While e-cigarettes eliminate combustion byproducts like carbon monoxide, they still deliver nicotine, which causes the same vasoconstrictive effects on wound healing. Vaping is not considered a safe alternative in the perioperative period.

What if I smoked right before my surgery date? Notify your surgeon immediately. Depending on how recently you smoked and the nature of your procedure, your surgeon may recommend postponing surgery to reduce the risk of serious complications.

Can anything reverse the effects of smoking on healing? Cessation is the most effective intervention. Beyond that, optimizing nutrition, hydration, and following rigorous post-operative wound care can help offset some — but not all — of the healing disadvantages associated with smoking history.

How does smoking affect scarring long-term? Even after a wound has closed, collagen remodeling continues for up to 12–18 months. Smoking during this period can impair remodeling, potentially resulting in scars that remain thickened, discolored, or raised longer than they would in a non-smoker.


Posted in blepharoplasty/eyelid surgery, Facelift, Revision rhinoplasty, rhinoplasty | Tagged , , , , , , , , , | Leave a comment

Silicone Nose Implant Removal: What You Need to Know


By Donald B. Yoo, M.D., F.A.C.S. | HALO Beverly Hills, Beverly Hills, CA

Silicone implants have been used in rhinoplasty for decades, particularly in Asian countries where dorsal augmentation is one of the most common goals of nose surgery. And while silicone is easy to carve, affordable, and initially well-tolerated, it carries a fundamental limitation: it is a foreign body, and the human body never fully accepts it.

Over time, that biological reality tends to catch up with patients.

Revision Rhinoplasty with Rib and DCF of previous Silicone Implant

Why Silicone Implants Fail

The most common problems I see in revision patients who come to me with existing silicone implants are:

  • Skin thinning over the implant
  • Visible or palpable implant edges
  • Implant migration or shifting
  • Capsular contracture causing distortion
  • In the most advanced cases — extrusion, where the implant begins to push through the skin

None of these are rare. They are the predictable, long-term natural history of a synthetic material placed in a location subject to constant movement, pressure, and the body’s ongoing foreign body response. In thin-skinned Asian patients, these problems often appear sooner and are more visible than in patients with thicker skin.

When Should an Implant Be Removed?

The short answer: when it is causing problems, or when there is clear evidence it will. I do not advise patients to remove a well-positioned, asymptomatic implant simply because time has passed. But when I see skin thinning, early visibility, shifting, or signs of chronic inflammation, I recommend removal — and sooner rather than later. Waiting until the implant extrudes or the skin is severely compromised makes reconstruction significantly more difficult.

What Happens After Removal?

This is the question patients are most anxious about, and understandably so. After years with an implant, the nose has adapted to the added volume. Removal alone leaves the patient without that structure, and in many cases with scarring, skin changes, and weakened support.

In my practice, implant removal is almost always combined with reconstruction using autologous tissue — meaning the patient’s own cartilage. Depending on what is available and what is needed, I use septal cartilage, ear cartilage, or rib cartilage. For dorsal augmentation, I have largely transitioned to diced cartilage fascia, or DCF — a technique that produces a smooth, natural-feeling dorsum that integrates with the surrounding tissue and carries none of the long-term risks of an implant.

The reconstruction is tailored to what the implant left behind. Some patients need straightforward dorsal replacement. Others require more extensive work — tip support, structural grafting, and soft tissue management — particularly when the implant caused significant scarring or deformity.

Is This a One-Stage or Two-Stage Procedure?

In most cases, I perform implant removal and reconstruction in a single operation. A two-stage approach — removing the implant, allowing the tissues to heal, then performing reconstruction — is reserved for cases involving active infection or severe skin compromise where it is not safe to place new grafts immediately.

Recovery and Results

Recovery from revision rhinoplasty after implant removal is generally longer than primary rhinoplasty, because the tissues have already been through surgery and have more scarring. Swelling resolves more slowly. I tell patients to expect 12 to 18 months before they see their final result — though meaningful improvement is visible much earlier.

The results, when done well, are transformative. Patients who spent years uncomfortable with a nose that looked or felt artificial consistently describe their reconstruction as the best surgical decision they ever made.

Choosing the Right Surgeon

Silicone implant removal and revision rhinoplasty is among the most technically demanding procedures in facial plastic surgery. The combination of altered anatomy, scar tissue, compromised skin, and the need for structural reconstruction requires a surgeon with specific experience in both revision rhinoplasty and autologous grafting techniques.

If you are living with a silicone nose implant that is causing concern — or simply wondering whether yours is still safe — I encourage you to schedule a consultation. An honest assessment now is far better than a crisis later.


Frequently Asked Questions

How do I know if my silicone nose implant needs to be removed?

The clearest signs are visible changes to the skin over the implant — thinning, redness, or a shiny appearance — or a shift in the implant’s position. You may also notice the edges of the implant becoming palpable or visible, or feel that the nose has become harder or more rigid over time. Any of these warrants a consultation. That said, you do not need to wait for symptoms to become serious before seeking an evaluation. Early intervention almost always leads to a better outcome than waiting until the implant has caused significant damage.

Can I just have the implant removed without replacing it?

In most cases, removal alone is not advisable. After years with an implant, the overlying skin has thinned and the underlying support structures have been altered. Simply removing the implant typically leaves the nose looking deflated, asymmetric, or structurally compromised. In the vast majority of my revision patients, removal is performed together with reconstruction using the patient’s own cartilage — which restores natural-looking volume and support without reintroducing the risks of a synthetic material.

Will I look worse after the implant is removed and reconstructed?

Not if the reconstruction is done well. Most patients are pleasantly surprised by how natural the result looks and feels compared to what they had with the implant. Autologous cartilage — particularly diced cartilage fascia for the dorsum — integrates with the surrounding tissue in a way that silicone never can. The nose moves naturally, feels natural, and ages naturally. The transition period during healing can be uncomfortable to navigate, but the long-term result is almost always a significant improvement.

How is revision rhinoplasty after implant removal different from my original surgery?

It is considerably more complex. Scar tissue from the original surgery changes the anatomy, limits tissue mobility, and increases the risk of complications. The skin may be thinner and less forgiving. Grafting requirements are typically greater. Recovery is longer. This is why surgeon selection matters enormously — revision rhinoplasty after implant removal is a subspecialty within a subspecialty, and outcomes vary widely depending on the surgeon’s experience with both revision cases and autologous reconstruction techniques.

How long is recovery after silicone implant removal and reconstruction?

Most patients are presentable within two to three weeks, though residual swelling — particularly at the tip — continues to resolve for 12 to 18 months. Because revision surgery involves scar tissue and more extensive dissection than primary rhinoplasty, swelling tends to linger longer. I advise patients to be patient with the process and to evaluate their final result at the one-year mark, not at one month.

Does insurance cover silicone nose implant removal?

In most cases, no — implant removal is considered an elective cosmetic procedure and is not covered by insurance. Exceptions may apply if there is documented infection, impending extrusion, or a medically necessary functional component to the surgery. During your consultation we can discuss the full scope of what is needed and provide transparent pricing.


Donald B. Yoo, M.D., F.A.C.S. is a double board-certified facial plastic surgeon and Medical Director of HALO Beverly Hills, specializing in revision and Asian rhinoplasty. His office is located at 433 N. Camden Drive, Suite 970, Beverly Hills, CA 90210. To schedule a consultation, visit www.donyoomd.com.

Posted in Asian rhinoplasty, rhinoplasty | Leave a comment

Can AI tell me what I need to improve my facial balance?

AI has made many of the questions we face on a daily basis easy to answer. The way AI alogorithms frame and organize responses help us to quickly consider the pertinent issues and formulate a decision. The value of AI comes from the fact that it can compile and synthesize information much more quickly than we can alone, but when it comes to making aesthetic recommendations, some limitations do present themselves.

AI chatbots such as Gemini, Claude, and ChatGPT can measure facial proportions and compare them to established canons of ideal proportions: vertical thirds, horizontal fifths, medial canthal to alar relationship, canthal tilt, et cetera. It can even take your photos and videos and generate simulations of potential changes that would mimic these more “ideal” facial proportions. While the results image may look great enough for you to share on your Instagram and Tik Tok, it doesn’t tell the full story.

Contemporary beauty standards can’t simply be distilled into a single set of measurements or a collection of angles. The Golden Ratio should be applied within the context of an individual patient’s anatomy, ethnicity and personal beauty standards and not simply on the amalgamation of hundreds of people considered “attractive” to determine a single defining algorithm.

An easier way to contextualize this would be to determine a perfect or Golden Ratio for the length of hair that makes a woman attractive. Some women look beautiful with short hair. Some women look beautiful with long hair. Many women look beautiful with hair that hair is any length in between. Now imagine taking the measurements of all these beautiful womens’ hair, averaging them, and calling those single average measurements the optimal hair length for beauty. As silly as it sounds, a hundred years ago when plastic surgery textbooks began creating these idealized ratios, measurements and angles for facial aesthetics, that’s exactly what they did. They simply chose individuals they felt were “attractive”, made measurements of their features, and spit out average numbers that then represented the gold standard of beauty.

Fast forward to today, and AI does essentially the same thing with your facial analysis. It can measure your face, compare to other averaged measurements of people considered beautiful, and tell you what is off. While it may provide some information, it lacks the context of your individual beauty ideals, anatomy and how this truly affects your facial balance outside of simple numbers.

Before AI Filter DY

After AI Filter DY

The other caveat of asking AI about facial balancing recommendations? AI does not make any accurate assessments of the bony and soft tissue anatomy. It’s easy to move pixels around on a digital image in 2 dimensions. Whether it’s possible to create the same effect in real life is a different story.

So for now, AI learning algorithms still have a ways to go before becoming as accurate as an experienced plastic surgeon focusing on facial balance and harmony rather than simple measurments.

Posted in chin augmentation, facial contouring, fillers, rhinoplasty | Tagged , , , , , , , | Leave a comment

The Cost of Asian Rhinoplasty in 2026: Complete Price Breakdown, Factors and Real Examples

Revision Asian rhinoplasty before and after using rib cartilage and diced cartilage fascia graft for natural dorsal augmentation and tip refinement
Before and After Revision Asian rhinoplasty with rib cartilage and diced cartilage fascia (DCF)

Asian Rhinoplasty Cost in Los Angeles: What to Expect in 2026

The cost of Asian rhinoplasty in Los Angeles typically ranges from:

$12,000 to $35,000+

This variation is not arbitrary. Pricing reflects differences in surgical technique, anatomical complexity, grafting requirements, and surgeon subspecialization in Asian nasal structure.

Unlike traditional reductive rhinoplasty, Asian rhinoplasty is primarily a structural augmentation procedure, often requiring cartilage grafting and advanced tip support. Whereas the goal in traditional rhinoplasty often includes removing a bump on the bridge of the nose (dorsal hump reduction) and reducing the size of the nasal tip to achieve refinement, goals that can be achieved easily achieved without the complexity of additional grafts and structural creation.


Why Asian Rhinoplasty Costs More Than Standard Rhinoplasty

Asian nasal anatomy presents distinct structural characteristics:

  • Thicker skin envelope
  • Lower dorsal height
  • Weaker lower lateral cartilage support

As a result, surgery often requires:

  • Dorsal augmentation
  • Tip projection with structural grafting
  • Cartilage harvesting (rib, septum, or ear)

These added steps increase operative time, technical complexity, and therefore cost.


Detailed Cost Breakdown (Los Angeles Market)

1. Surgeon’s Fee ($8,000 – $25,000+)

The largest cost component is the surgeon’s fee, which reflects:

  • Experience in Asian rhinoplasty specifically
  • Case complexity (primary vs revision)
  • Use of advanced structural techniques

Subspecialists in ethnic rhinoplasty typically command higher fees due to greater technical demand and outcome consistency.


2. Anesthesia Fees ($1,500 – $3,500)

Asian rhinoplasty is usually performed under general anesthesia, particularly when rib cartilage is used. Longer operative times increase anesthesia costs.


3. Facility Fees ($1,500 – $5,000)

Costs vary depending on:

  • Accredited surgical center vs private suite vs hospital
  • Duration of surgery
  • Level of staffing and monitoring

4. Cartilage Grafting (Major Cost Driver)

Rib Cartilage (Most Expensive)

  • Adds $3,000 – $8,000+
  • Required for:
    • Moderate to significant augmentation
    • Moderate to significant nasal tip/alar definition
    • Revision surgery
  • Advantages:
    • Strong structural support
    • Lower long-term complication rates
    • Most effective for achieving optimal refinement in thicker skinned patients

Septal Cartilage

  • Limited availability in many Asian patients
  • Typically used in less complex cases or for patients seeking minimal change

Ear Cartilage

  • Used for contour refinement rather than major support

Primary vs Revision Asian Rhinoplasty Cost

Primary Asian Rhinoplasty

$12,000 – $25,000+

  • First-time surgery
  • Moderate structural augmentation

Revision Asian Rhinoplasty

$20,000 – $35,000+

  • Scar tissue and altered anatomy
  • Deficient or deformed cartilage from previous surgery
  • Frequent need for rib cartilage
  • Increased operative complexity

Revision cases are consistently more expensive due to unpredictability and surgical difficulty.


Implant vs Rib Cartilage: Cost vs Long-Term Value

Silicone Implant Rhinoplasty

Lower upfront cost

  • Shorter surgery
  • Simpler technique

However:

  • Higher risk of infection, extrusion, and long-term complications
  • Increased likelihood of revision surgery
  • Unnatural appearance long-term with thinning of nasal skin

Rib Cartilage Rhinoplasty

Higher upfront cost

  • More complex procedure

But:

  • Superior biocompatibility
  • More natural aesthetic outcome
  • Lower long-term complication rate

From a health economics perspective, structural rhinoplasty often represents greater long-term value despite higher initial cost.


What Is Included in the Cost?

Most Los Angeles practices include:

  • Surgeon’s fee
  • Anesthesia
  • Operating facility
  • Standard postoperative visits

May also include:

  • Imaging or surgical planning tools
  • Medications
  • Limited revision policy

Always confirm details with your surgical quote following consultation with your potential surgeon.


How to Choose the Right Surgeon (Not Based on Price Alone)

When evaluating Asian rhinoplasty cost in Los Angeles, prioritize:

  • Documented experience in Asian nasal anatomy
  • Consistent, natural-looking outcomes
  • Structural (not purely cosmetic) approach
  • Transparent explanation of grafting strategy

Lower-cost procedures frequently correlate with:

  • Inexperience with Asian aesthetics
  • Simplified use of rib cartilage grafts i.e. en bloc rib grafts or diced cartilage glue (DCG) grafts instead of unified tip grafting with diced cartilage fascia (DCF) grafts
  • Reliance on cadaveric rib, which has a much higher risk of resorption than your own rib cartilage
  • Use of implants
  • Limited structural support
  • Higher revision rates

Frequently Asked Questions

How much does Asian rhinoplasty cost in Los Angeles?

Most patients pay between $12,000 and $35,000+, depending on complexity and technique.

Why is Asian rhinoplasty more expensive?

It requires augmentation, cartilage grafting, and structural reinforcement, increasing operative time and technical demand.

Is rib cartilage worth the extra cost?

In the right hands, yes. It provides better long-term stability and lower complication rates, particularly in complex or revision cases. Rib cartilage, however, is simply a building block. The surgeon’s expertise and artistry are critical to using that building block to create the most aesthetically beautiful nose for your individual face.

Is Asian rhinoplasty covered by insurance?

No. Cosmetic procedures are not covered, though functional components may be partially reimbursed if medically necessary.


Final Thoughts: Cost Reflects Complexity and Expertise

Asian rhinoplasty is a highly specialized procedure requiring:

  • Structural engineering of the nasal framework
  • Ethnic preservation
  • Advanced grafting techniques

As a result, cost variation is expected and appropriate.

Patients should evaluate cost in the context of surgeon expertise, technique selection, and long-term outcome reliability, rather than viewing price as an isolated factor.

Learn more: https://www.donyoomd.com/blog/2025/11/14/whats-the-biggest-challenge-in-asian-rhinoplasty/


Before and After Asian rhinoplasty with unified rib cartilage grafts and diced cartilage fascia (DCF).
Before and after revision rhinoplasty with unified rib cartilage grafts and diced cartilage fascia to create a more refined and balanced nose.

Posted in Asian rhinoplasty, rhinoplasty | Tagged , , , , | Leave a comment

Red Light Therapy: Mechanisms, Clinical Applications, and Evidence-Based Considerations

Red light therapy (RLT), or photobiomodulation (PBM), has emerged as a non-thermal, light-based modality with growing support in the biomedical literature. Its clinical relevance spans dermatology, wound healing, and regenerative medicine. As interest expands, it is important to distinguish between theoretical mechanisms, demonstrated clinical effects, and the parameters required to achieve reproducible outcomes.

What Is Red Light Therapy?

Red light therapy involves exposure to visible red (approximately 620–700 nm) and near-infrared (700–1100 nm) wavelengths. These wavelengths penetrate tissue and are absorbed by intracellular chromophores, most notably cytochrome c oxidase within the mitochondrial respiratory chain.

This interaction has been associated with:

  • Increased adenosine triphosphate (ATP) production
  • Modulation of reactive oxygen species (ROS)
  • Activation of transcription factors involved in cellular repair

These mitochondrial mechanisms and downstream signaling cascades are well-described in the literature (Hamblin, 2017; Avci et al., 2013).

Biological Effects on Skin and Connective Tissue

Experimental and translational studies suggest that red and near-infrared light influence multiple pathways relevant to skin physiology:

  • Upregulation of collagen synthesis via TGF-β–mediated pathways
  • Enhanced dermal remodeling and extracellular matrix organization
  • Increased angiogenesis and microcirculation
  • Reduction in inflammatory signaling

In human clinical studies, photobiomodulation has demonstrated improvements in skin complexion, collagen density, and wrinkle reduction (Barolet et al., 2016; Avci et al., 2013).

Clinical Applications

Dermatologic and Aesthetic

  • Photoaging and fine rhytides
  • Skin laxity and textural irregularities
  • Acne vulgaris and inflammatory dermatoses
  • Post-procedural recovery

Wound Healing and Regenerative Medicine

  • Chronic wounds and soft tissue injury
  • Scar modulation

Musculoskeletal and Pain Applications

  • Tendinopathy and soft tissue pain syndromes

Systematic reviews and meta-analyses suggest that PBM can improve pain and functional outcomes in soft tissue conditions, although heterogeneity in protocols remains a limitation (Tripodi et al., 2021).

Treatment Parameters and Dose-Response Relationships

A defining feature of photobiomodulation is its sensitivity to treatment parameters. Key variables include:

  • Wavelength: Determines tissue penetration and chromophore interaction
  • Irradiance (power density): Governs rate of energy delivery
  • Fluence (J/cm²): Total delivered energy
  • Treatment timing and frequency: Influences cumulative biological response

PBM follows a biphasic dose-response relationship (Arndt–Schulz law), in which insufficient energy yields minimal effect, while excessive exposure may attenuate therapeutic benefit (Hamblin, 2017).

At-Home Devices: Limitations in Context

Consumer-grade devices have improved accessibility; however, several limitations are frequently cited:

  • Lower and inconsistent energy output
  • Limited transparency in wavelength specificity and dosimetry
  • Variability in manufacturing standards
  • Lack of protocol standardization

Given the dose-dependent nature of PBM, these factors can influence reproducibility and clinical efficacy.

Clinical-Grade, In-Office Treatment: Where It Differs

From a scientific and clinical standpoint, the distinction between at-home and in-office treatment is primarily related to control of variables known to influence biological response.

  • Reproducible dosimetry: Energy delivery aligned with studied therapeutic ranges
  • Adequate irradiance: Sufficient power density for deeper tissue targets
  • Protocol standardization: Alignment with published clinical parameters
  • Integration with procedures: Use as an adjunct to lasers, microneedling, or surgery
  • Clinical oversight: Adjustment based on patient-specific variables

These factors are particularly relevant given that most high-quality studies demonstrating efficacy are conducted using controlled clinical devices.

Facial Plastic Surgery Applications

  • Reduction of postoperative edema and ecchymosis following rhinoplasty and blepharoplasty
  • Acceleration of re-epithelialization after laser resurfacing
  • Improvement in scar quality following incisional procedures

Emerging evidence suggests photobiomodulation may enhance postoperative recovery through modulation of inflammation and microcirculation.

Conclusion

Red light therapy represents a scientifically grounded modality with demonstrated effects on cellular metabolism, inflammation, and tissue repair. Its clinical utility continues to expand as higher-quality trials refine optimal treatment parameters.

While at-home devices may offer convenience, the strongest evidence base supporting photobiomodulation derives from controlled, clinical-grade applications.

References

  • Avci, P., et al. (2013). Low-level laser (light) therapy (LLLT) in skin: Stimulating, healing, restoring. Seminars in Cutaneous Medicine and Surgery, 32(1), 41–52. https://doi.org/10.12788/j.sder.0007
  • Barolet, D., et al. (2016). In vivo human dermal collagen production following LED-based therapy. Journal of Cosmetic and Laser Therapy, 18(2), 93–99. https://doi.org/10.3109/14764172.2015.1054634
  • Hamblin, M. R. (2017). Mechanisms and applications of the anti-inflammatory effects of photobiomodulation. AIMS Biophysics, 4(3), 337–361. https://doi.org/10.3934/biophy.2017.3.337
  • Tripodi, N., et al. (2021). Photobiomodulation in tendinopathy: A systematic review and meta-analysis. BMC Sports Science, Medicine and Rehabilitation, 13, 96. https://doi.org/10.1186/s13102-021-00306-z

Posted in Healing/Recovery, Lasers/Skin Care | Tagged , , , , , | Leave a comment

Is there a difference between K beauty skincare and American skincare?

Korean moisturizers place an emphasis on products that hydrate the skin while leaving a texture that remains light to the touch. Rather than trying to combine all the the ingredients in a single product as American moisturizers sometimes do, Korean skincare relies on a layered, multi-step approach to achieve both high hydration and skin barrier support while maintaining a non-occlusive and lightweight finish.

American skincare products tend to utilize higher levels of occlusives, which help protect dry and damaged skin, but may also feel “heavy” at times. Korean moisturizers often employ gels and gel-cream hybrid emulsions to achieve significant hydration while minimizing greasiness.

The disparity in regulatory environment between the U.S. and Korea also represents an important distinction between American and Korean moisturizers. Korea tends to have a regulatory environment more conducive to innovation and more efficient in allowing companies to translate their research and development into consumer-facing products. This allows Korean manufacturers to take advantage of unprecedented delivery systems and novel active ingredients faster than practically any other modernized country.

Why is salmon sperm showing up in skincare?

The basis of skin repair and hydration comes from the DNA fragments call PDRN (polydeoxyribonucleotide) that are isolated from salmon sperm. PDRN was originally investigated for its potential benefits in tissue repair and wound healing – such as patients with non-healing diabetic ulcers. Eventually the positive effect on cellular repair processes was applied to aesthetic medicine to improve the appearance of skin.

What are the potential benefits of using PDRN serums?

The most immediate benefit of PDRN serums is improved hydration, as the PDRN fragments are very effective at attracting and retaining moisture, creating a more dewy and luminous skin tone. With repeated use, skin texture and elasticity improves as the collagen support becomes augmented and the integrity of the skin barrier improves.

What, exactly, doesPDRN do? (Specifically, *how* does it work to promote the aforementioned benefit(s)?)

PDRN stimulate skin repair and collagen synthesis by interacting with receptors which activate fibroblast (skin cell) activity, driving the recovery of dermal injury and the synthesis of new collagen and elastin (the proteins giving firmness and elasticity to skin). Studies have also shown PDRN to have effects on reducing inflammation and redness by reducing the expression of inflammatory cytokines.

Posted in Lasers/Skin Care, salmon dna, Skin Boosters | Tagged , , , , , , , | Leave a comment

A Guide on How to Analyze a Plastic Surgeon’s Before and After Photos

We are in an unprecedented era of visibility for aesthetic procedures. Anyone can go online and have immediate access to before and after photos, videos, and even procedure vlogs documenting the whole process from consultation to recovery. How then is a patient supposed to critically analyze this huge volume of content accurately? Read on to learn some insider information.

  1. Check the Lighting
    • You may assume the lighting conditions between the before and after photos are the same, but you’ll be suprised just how many surgeons try to pass off changes in lighting to actual surgical improvements in a patient’s appearance. Overhead lighting can accentuate shadows on a patient’s face while bright and diffuse lighting can eliminate shadows – think tear troughs and dark under eye circles, or photos showing skin quality. The best way to check for lighting is the patient’s complexion and the catchlights in a patient’s eyes. If the patient’s complexion does not look consistent from before to after photo, start being skeptical that the lighting has not stayed consistent. From there, look carefully at the reflection in the patient’s eyes. Is the light source symmetric on both sides of the face and the same as the after photos? Only when you see that can you be sure that the lighting is consistent between before and after photos.
  2. Check the Angles
    • Images should be taken from the same distance, at the same level, and same angle every time. Plastic surgeons are notorious for using facelift before and after photos where the patient has the chin down to scrunch neck wrinkles while the neck is extended in after photos to make the results look even more spectacular. The angle that a frontal view photo is taken can drastically alter the appearance of the eyes, nose and jawline to create the illusion of slimming and tapering and vice versa.
  3. Evaluate the Entire Body of Cases
    • A single successful photo is not enough to judge surgical skill. Look for:
    • Consistency: Multiple patients with similar outcomes indicate reproducibility. Ideally being able to identify before and afters of other patients with similar baseline anatomy or outcomes similar to your aesthetic ideals will bode favorably for the surgeon’s potential of success with your face.
    • Variety: A surgeon experienced with diverse facial anatomies demonstrates versatility and adaptability.

Analyzing before-and-after photos is both an art and a science. By focusing on photographic consistency, symmetry, subtle details, authenticity, and reproducibility, patients can make informed decisions while understanding realistic outcomes. Always approach these images critically, and use them as one of several tools to evaluate a surgeon’s expertise.

Posted in facial contouring, Procedures, rhinoplasty | Tagged , , , , , | Leave a comment

My upper eyelids feel heavy and it feels like the skin is sagging. Do I need an upper blepharoplasty or browlift?

The periorbital area includes the upper eyelids and the eyebrows, and the interplay between the two anatomic units is important in creating a comprehensive rejuvenation to the eyes. For most patients the eyebrow position looks most aesthetically pleasing when the lateral aspect is level or slightly higher than the medial aspect, and the body of the eyebrow sits at or slightly above the supraorbital rim or brow bone. When the eyebrows are positioned higher than the brow bone it can lead to a startled or surprised appearance, while a position inferior or lower than the brow bone can contribute to an stern, angry or aged appearance. When the eyebrows are ptotic, the eyebrow skin may encroach on the upper eyelids or displace the upper eyelid skin inferiorly to create a hooded and heavy appearance to the upper eyelids.

When assessing the upper eyelids, the eyebrows must first be evaluated for their relative position. Once the normal position of the eyebrows has been established, then the surgeon may accurately assess the degree to which the upper eyelid skin is lax or redundant and can make a precise measurement in terms of the amount of skin removal. When the eyebrows are ptotic or droopy at their medial aspect, then an endoscopic browlift, direct browlift or coronal browlift may be indicated, depending on the patient’s anatomy and aesthetic goals. When the lateral brow is ptotic without accompanying ptosis of the medial brow, a temporal browlift may be most appropriate.

A temporal browlift involves incisions behind the temporal hairline bilaterally, and when executed precisely will not result in any change to the appearance of the hairline or alopecia. Within 3-6 months hair will typically grow through the incision and camouflage it completely. Through this hidden incision skin may be removed and dissection performed down to the orbital rim to release the connections tethering and pulling down on the brow. The same incision can be used to create further dissection into the midface and cheeks to perform and endoscopic facelift. In that instance suspension sutures are used to elevate the soft tissue and skin along the midface and, depending on the patient, the lateral canthus of the eyes, along with the brow/upper eyelid complex. In a temporal browlift the suspension sutures secure the mobilized skin/muscle/fascia flap to the deep temporalis fascia, creating a more open and refreshed appearance to the eyes. The elevation of the brows and brow skin allow for elevation of the supratarsal crease even when upper eyelid skin has not been surgically removed.

Before and after temporal browlift
Before and After Temporal Browlift

Posted in Browlift, Endoscopic Facelift | Tagged , , , , , | Leave a comment