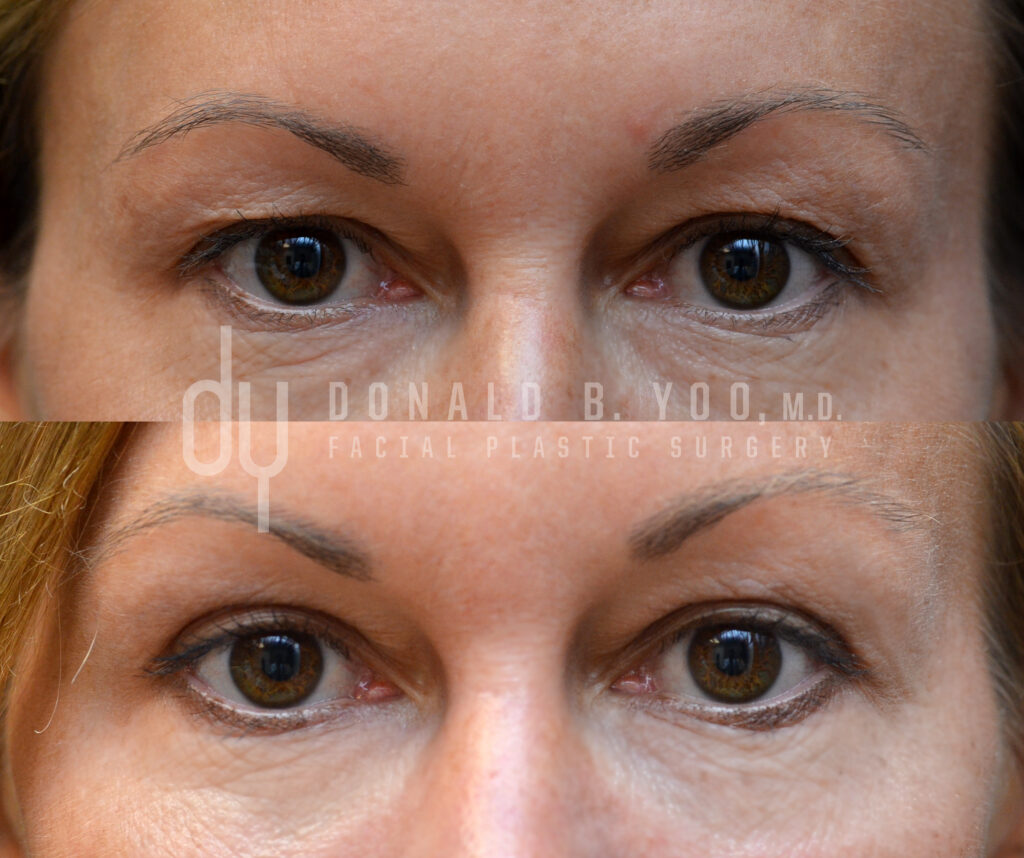
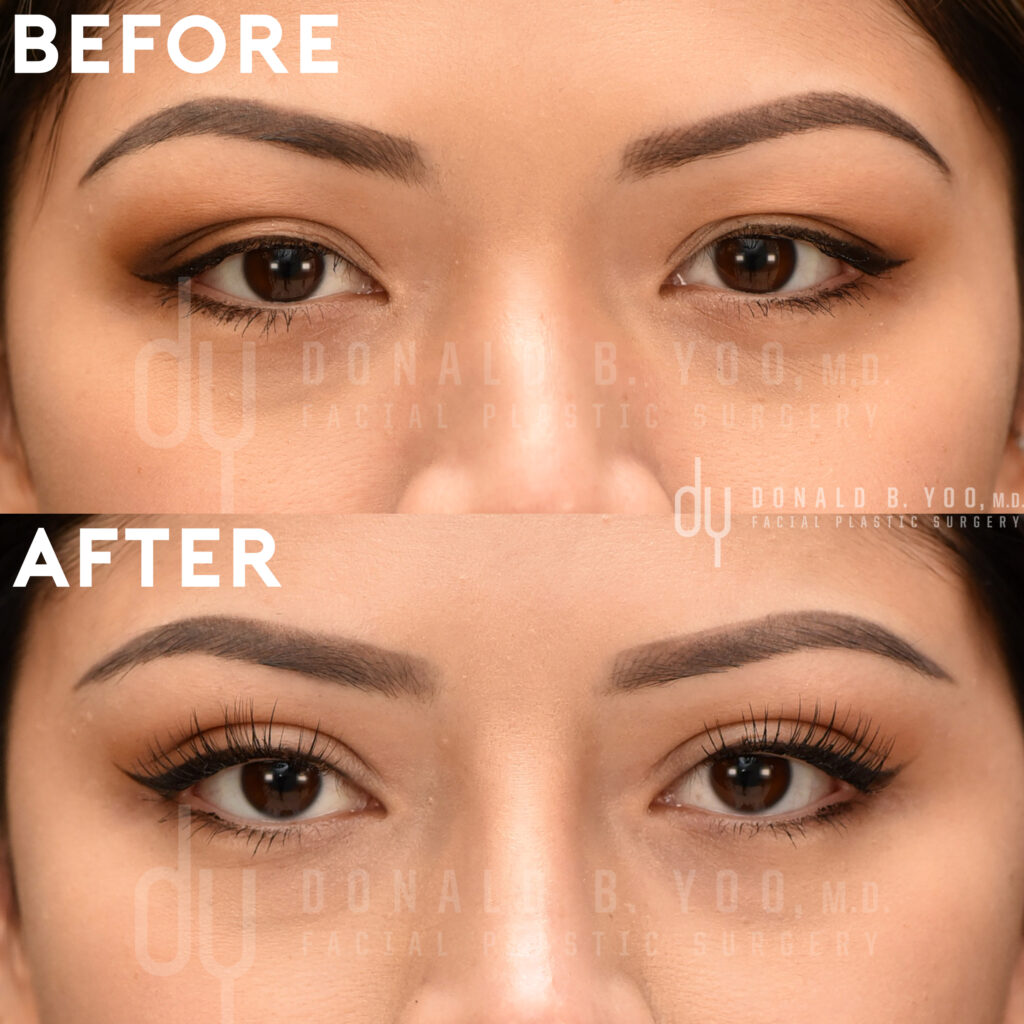
Blepharoplasty refers to any surgery that reshapes the eyelid, while standard upper blepharoplasty and Asian upper blepharoplasty require different techniques owing to some anatomic differences unique to Asian eyelids. For a standard upper blepharoplasty procedure, excess skin (dermatochalasis) will cause sagging and droopiness of the upper eyelid, creating a tired and aged appearance. During upper blepharoplasty an incision or cut is made through the skin where the eyelid crease is, and the excess skin is removed. Occasionally excess fat between the upper eyelid and brow will be removed or repositioned to reshape the appearance of the upper eyelid sulcus, though this is performed in the minority of cases. Once excess skin, and occasionally excess fat, is appropriately addressed, the skin is closed. In contrast, during Asian blepharoplasty specific attention must be directed at re-establishing the connection between the tarsal plate and/or levator aponeurosis to the dermis of the skin. This connection is responsible for setting the height and shape of the upper eyelid crease and is created by a surgical technique called supratarsal fixation, during which the operating surgeon precisely anchors the crease at multiple points to establish this connection. It is during this phase the surgeon can create an infold, or tapered crease that meets the corner of the eye, or an outfold or parallel crease that runs parallel with the eyelid margin and allows for space between the upper eyelid crease and eyelid margin for the upper eyelid to show (where eye shadow would be applied).
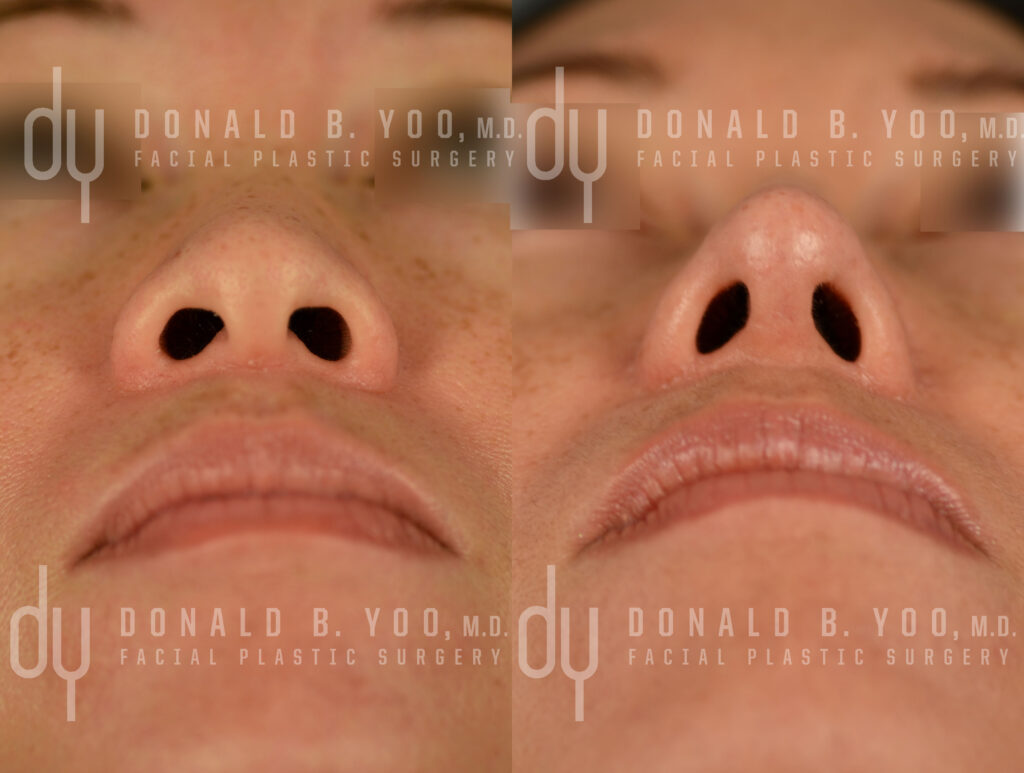
Alarplasty by Rhinoplasty Specialist Dr. Donald B. Yoo
Key takeaways
Alarplasty, alar base reduction and alar base modification are surgery to reshape the ala (the nostril wings) and nostrils, alone or combined with rhinoplasty.
The ala is made of skin and fibrofatty tissue and has no cartilage, so its size and shape depend on skin thickness and the configuration of the tip cartilage.
Before planning incisions, your surgeon assesses tip projection and width, infratip and columella length, ala width and flare, and the size and shape of the nostril opening.
Alarplasty, alar base reduction and alar base modification refer to a surgical procedure used to reshape the ala and nostrils, alone or in combination with rhinoplasty, to improve and enhance the overall proportions of the nose. The ala and alar rims are the subunit of the nose that are commonly referred to as the nostrils. Skin and fibrofatty tissue comprise the ala and nostrils, and this nasal subunit actually lacks any cartilage. Given this, the size and shape of the ala is intricately tied to the patient’s skin thickness, as well as the anatomic configuration of the lower lateral cartilage (tip cartilage).
Alarplasty Alar Base Reduction Explained
During alarplasty, your surgeon will assess the proportions of your nose, in terms of the tip projection, tip width, length of infratip, length of columella, the width of the ala and nostrils, the flare of the ala and nostrils, and the size and shape of the nostril aperture. All these aspects factor into the placement and design of alarplasty incisions, with some incision placements favoring more reduction of width (sill incisions) while other incision designs (Weir incisions) will favor greater flare reduction. Preserving the natural curvature of the ala and nostril, while optimizing the proportions between the projection, width of the nose and the infratip:columellar ratio will ensure a natural appearing, successful outcome.
Alarplasty, also called alar base reduction, narrows the alar base and reduces nasal flaring. It is a rhinoplasty technique that has grown in popularity over the last decade (Cordero and colleagues, 2025). It can be performed on its own or at the same time as rhinoplasty, and its aim is a lower third of the nose whose width and nostril shape suit the rest of the face.
Why the nostrils are judged in motion as well as at rest
Nostrils do not stay still. In a study of 150 Asian women recorded with dynamic three-dimensional imaging, researchers compared the resting face with the face at maximum smile and measured how much the alar flaring and the alar base moved. Three senior plastic surgeons and a machine-learning clustering analysis each sorted the participants into three classes of movement, and the two methods agreed (Zhong and colleagues, 2023). The authors concluded that these classes can give surgeons referenced, quantitative parameters when deciding on treatment, and that treatment is not recommended for patients in the lowest class of movement.
In practice this means a careful evaluation looks at your nose at rest, when you smile and from several angles, not only in a single still photograph. Ask your surgeon how they assess motion.
Questions to ask before alarplasty
How do you decide which incision is right for my nostrils: the alar base, the nasal sill, or both?
Where will the incision sit relative to the alar-facial groove, and how will the scar look when healed?
Is alarplasty alone enough for me, or do my skin thickness and tip cartilage shape mean other changes are needed?
Can I see before and after photos of patients with a nose like mine, including smiling photos?
References
Cordero JJ, Mehdizadeh M, Garbaccio N, et al. Alarplasty: a bibliometric analysis of the top 50 cited articles in alar base reduction techniques. Aesthetic Plastic Surgery. 2025;49(23):6453-6459. PubMed.
Zhong Y, Zhou S, Xie A, et al. Classification of alar dynamic aesthetic in an Asian female population: experts or automatic algorithms? Aesthetic Plastic Surgery. 2023;47(2):757-764. PubMed.
Written and medically reviewed by Donald B. Yoo, M.D., F.A.C.S., facial plastic surgeon in Beverly Hills.
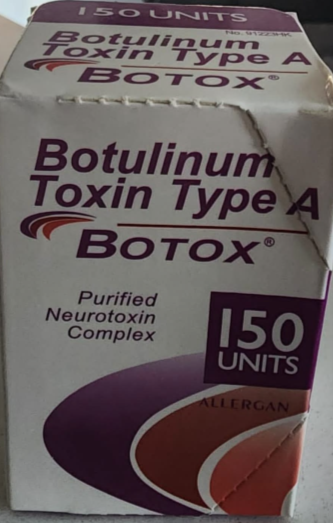
One of the leading cosmetic injectables has recently come into the national spotlight after the Centers for Disease Control announced an investigation, jointly with the U.S. Food and Drug Administration, and several state and local health departments, into 22 cases over 11 states of people reporting harmful reactions after receiving botulinum toxin injections from un-licensed providers in non-healthcare settings such as spas. Harmful reactions from these unlicensed Botox injections have been reported in California, Colorado, Florida, Illinois, Kentucky, Nebraska, New Jersey, New York, Tennessee, Texas, and Washington.
Although the investigation is ongoing, the CDC has found that at least in some of these cases the botulinum toxin injected was counterfeit Botox, and in all cases the injections were performed by non-physician providers in non-healthcare settings such as homes and spas. The CDC went on to report that 55% of those harmed required hospitalization, with symptoms such as: blurry vision, drooping eyelids, difficulty swallowing, dry mouth, slurred speech, difficulty breathing, fatigue, and generalized weakness.
Counterfeit Botox Packaging
The CDC and FDA are instructing consumers to confirm with your health care professional that you are receiving a product from an authorzied source and to ask your health care professional if they are licensed and trained to administer the product. This may sound like common sense, because it is, and this represents the absolute minimum standard to provide cosmetic Botox and neuromodulator injections. As a consumer, the best way to ensure the safest and most beautiful results is to seek out a board-certified facial plastic surgeon, plastic surgeon or dermatologist’s office to ensure all providers have the adequate credentials, training and experience to perform cosmetic injections.
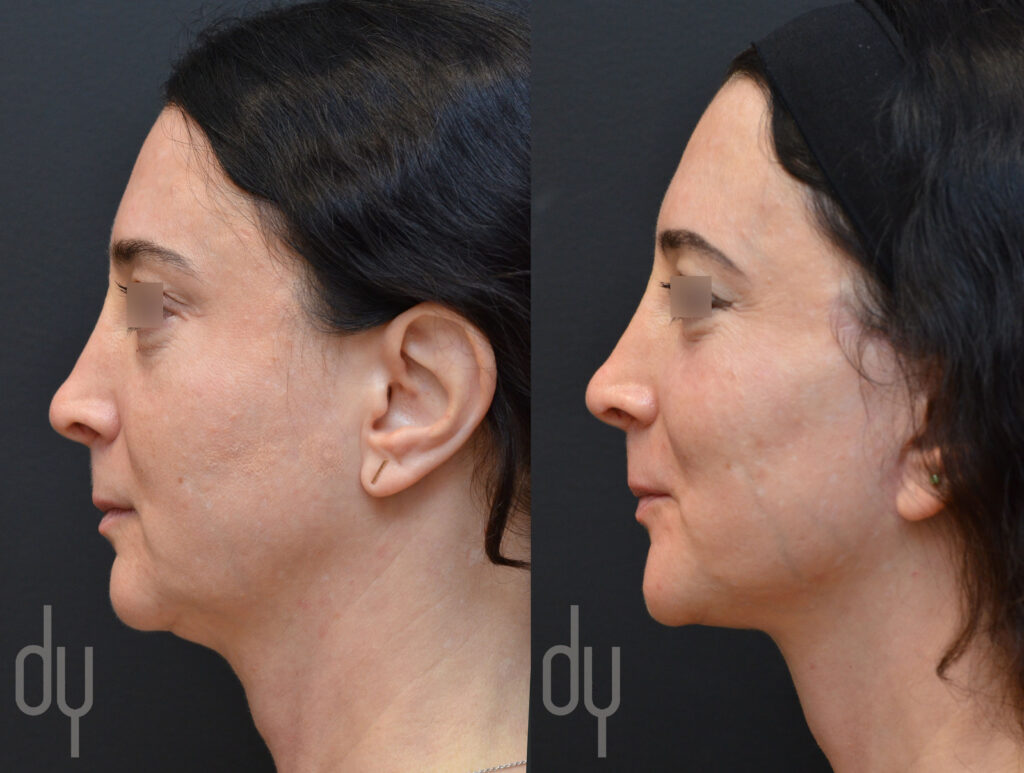
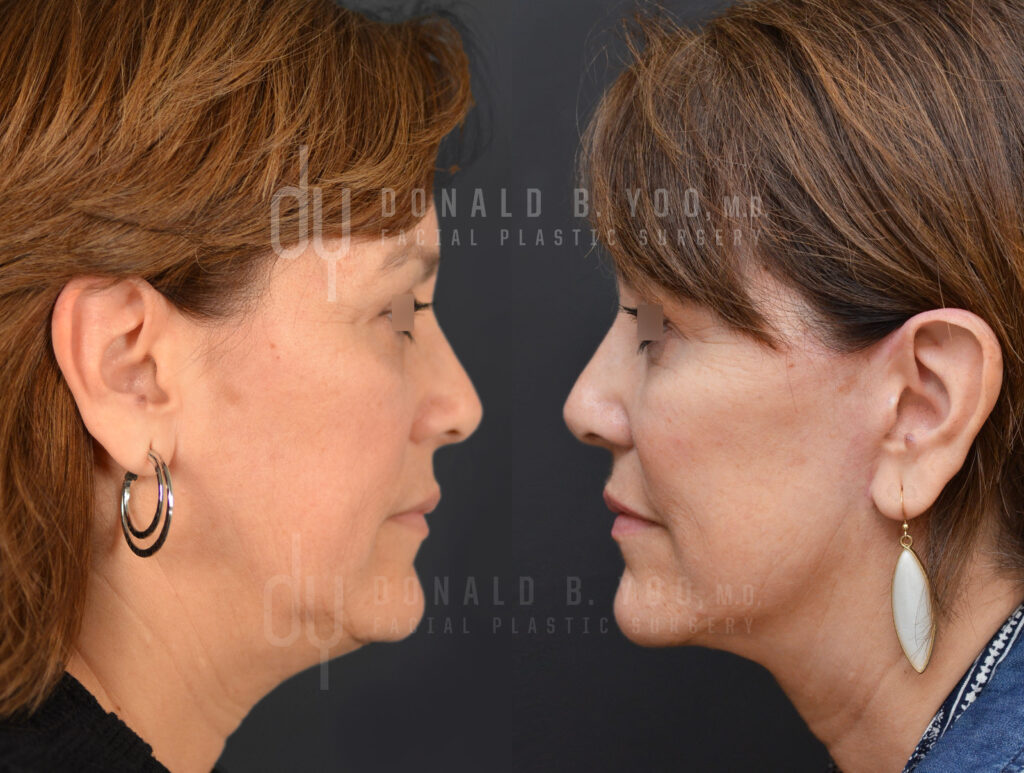
The aging process is continual, and a neck lift is a surgical procedure to address and improve some of the signs of aging along the neckline and jawline. Typically the results of a neck lift will last ten to fifteen years, while maintenance with a good skincare routine and proper noninvasive treatments will help to extend this duration.
Neck lift and deep-plane facelift by Donald B.Yoo, M.D.
What is the best age for a neck lift?
The best age for a neck lift is when laxity in the skin and soft tissue of the neck and face begin creating sagging along the neck line or jowling along the jaw line. The majority of patients will seek treatment in their 40s to 50s, though depending on genetics and lifestyle this spectrum may widen to include patients in their 30s as well.
Is a neck lift painful?
Neck lifts do create some discomfort initially due to the tightening of previously lax skin and soft tissue along the neck and lower face, but are generally not painful. Typically the discomfort will largely resolve within the first week as much of the swelling resolves, and most patients will be able to return to light exercise after two weeks.
Why are neck lifts so expensive?
The cost of a neck lift and face lift will depend on patient-specific factors such as baseline anatomy and aesthetic goals which determine the complexity and breadth of the surgery, and also on the experience and skill-level of the facial plastic surgeon.
Are you awake during neck lift surgery?
Neck lift surgery may be performed as an awake procedure under local anesthesia and sedation, or it can be performed under general anesthesia. For most patients, general anesthesia represents the safer and more comfortable treatment option, but some surgeons may be reluctant due to the more stringent requirements of a certified surgery center and the need for an anesthesiologist. Be sure to discuss the pros and cons of each with your surgeon to determine what time of anesthesia is best for you.
Can I tighten a saggy neck without surgery?
Yes! One of the marvels of modern medicine is the availability of nonsurgical skin tightening and nonsurgical neck lifting procedures to help address the signs of aging with minimal downtime and without any signs of surgery. Noninvasive and nonsurgical face lift involves the use of energy delivered to the deep layers of the skin and subcutaneous tissue to create tightening and re-organization of collagen and elastin. Some of the most effective devices in the market today include: Potenza, which uses RF (radiofrequency energy) delivered through an array of micro-needles, Ulthera, which uses high-frequency ultrasound, and OligioX, which relies on precise RF delivery to multiple layers of skin.
Before and After Revision rhinoplasty with rib cartilage with Dr. Donald B. Yoo to refine the nasal tip and to eliminate a pollybeak deformity.
Revision rhinoplasty is a nose job surgery performed in the setting of a previous, or multiple previous, rhinoplasty surgeries that have left a patient with aesthetic and/or functional issues. The aim of revision rhinoplasty and revision nose job surgery is to restore normal function while enhancing the shape and appearance of the nose.
Is revision rhinoplasty a good idea?
Appropriate candidacy for revision rhinoplasty or revision nose job surgery is best assessed by a rhinoplasty surgeon specializing in revision rhinoplasty surgery. The goals for a revision rhinoplasty must be congruent and attainable for a patient to be a good candidate for revision nose job surgery, which can only be determined after thorough evaluation and comprehensive consultation with an experienced revision rhinoplasty surgeon.
What is the success rate of revision rhinoplasty?
Multiple publlished stuides have attempted to determine the revision rate after rhinoplasty and revision rhinoplasty, and the revision rate typically ranges between 10%-20%. While the true number may be difficult to accurately ascertain, one thing is clear from these studies – the rate of dissatisfaction and desire for revision surgery is far higher for rhinoplasty and revision rhinoplasty than for the majority of other surgical procedures. This is partly due to the complexity of the operation itself, partly the expectations of highly motivated patients seeking elective cosmetic surgery, and partly the technical prowess of the surgeon performing the rhinoplasty. Paramount to success is careful patient selection by the surgeon, and careful surgeon selection by the patient, so that the patient’s expected idealized outcome is coherent with the rhinoplasty surgeon’s experience, technical abilities, and aesthetic eye.
Before and after revision rhinoplasty with rib cartilage to create greater straightness and symmetry to the nose.
Asian rhinoplasty is surgery that reshapes the nose with techniques that add structural integrity, definition and refinement, often using cartilage or tissue in addition to what is already in the nose.
When Asian rhinoplasty is performed with tissue from your own body (autologous grafts), the result is permanent: the grafts are living tissue that becomes part of the nose.
If synthetic implants are used, they will eventually need to be removed, because they can thin the skin, become visible or extrude.
Asian rhinoplasty, when performed with tissue from your own body (autologous grafts) is permanent. One of the great benefits of autologous grafts are that they are viable, living tissue from your own body, so there is no risk of rejection or resorption as the tissue will be fully incorporated into your nose. If Asian nose job surgery is performed with synthetic implants, then those implants will have to be removed at some point as they will eventually thin the skin and become visible, or even extrude.
What is an Asian nose job rhinoplasty surgery?
Asian rhinoplasty or Asian nose job, is a specific type of surgery to reshape the nose with techniques providing increased structural integrity to the nose while adding definition and increasing refinement. Asian rhinoplasty techniques often demand the use of cartilage and/or tissue in addition to what is available in the nose to supplement the strength of the nasal framework to reshape the overlying skin. Rib cartilage and diced cartilage fascia (DCF) are common autologous grafts used to reshape the nose in a permanent fashion.
What is Korean nose job surgery?
Koreans tend to have slightly thinner skin than other Asian patients, while still retaining a relative lack of strength of the nasal cartilage (tip cartilage and septal cartilage). This combination presents a distinct set of challenges for the Asian rhinoplasty surgeon to address, as projection and support must be added to the nose in a way that maintains delicate tip and dorsal (nasal bridge) aesthetics while providing a permanent result.
Permanent is not the same as risk-free
Your own tissue brings real advantages, but it comes with its own risks, and a good surgeon will tell you about them. Complications reported with costal (rib) cartilage include warping, infection and displacement, as well as problems at the harvest site such as pneumothorax, pain and chest scars. Many of these can be minimized by following recommended techniques (Won and Jin, 2020).
Infection is a good example of how experience varies. In a retrospective review of 2,630 rhinoplasties in an East Asian population by a single surgeon over 16 years, the infection rate was 3.39% in cases using autologous costal cartilage. Infection was about 19 times more likely after revision than after primary surgery (3.63% versus 0.19%), and women were 3.6 times as likely to develop an infection (Tran and Jang, 2022). A review of 363 consecutive septorhinoplasty patients in a single private practice found an overall infection rate of 3.0%, with 4.0% in primary and 2.1% in revision cases. In that study, patient risk factors alone did not reliably predict who would develop an infection, and knowing a patient’s endogenous nasal flora helps to further reduce infectious complications (Yoo and colleagues, 2015). These are different patient groups treated by different surgeons, so the figures are not directly comparable.
Implants carry their own risks. Alloplastic implants are used much more commonly than autologous tissue in many Asian countries, and the reported complications include infection, extrusion, movement, irregularities, absorption, prolonged swelling, seroma and contracture (Choi, 2020).
Questions to ask about grafts and implants
Which material do you recommend for my nose, and why?
What are the risks of that material, including infection, shifting and the chance I might need another operation?
If I choose an implant, what is the plan if it ever needs to be removed?
How many revision cases do you treat, and how do you prevent and manage infection?
References
Won TB, Jin HR. Complications of costal cartilage Asian rhinoplasty and their management. Facial Plastic Surgery. 2020;36(5):528-538. PubMed.
Choi JY. Complications of alloplast rhinoplasty and their management: a comprehensive review. Facial Plastic Surgery. 2020;36(5):517-527. PubMed.
Tran KN, Jang YJ. Incidence and predisposing factors of postoperative infection after rhinoplasty: a single surgeon’s 16-year experience with 2630 cases in an East Asian population. Plastic and Reconstructive Surgery. 2022;150(1):51e-59e. PubMed.
Yoo DB, Peng GL, Azizzadeh B, Nassif PS. Microbiology and antibiotic prophylaxis in rhinoplasty: a review of 363 consecutive cases. JAMA Facial Plastic Surgery. 2015;17(1):23-27. PubMed.
Written and medically reviewed by Donald B. Yoo, M.D., F.A.C.S., facial plastic surgeon in Beverly Hills.
Asian rhinoplasty represents a unique subset of rhinoplasty surgery that requires specialized technical expertise and an aesthetic eye that is finely in-tune with Asian beauty standards. While a standard rhinoplasty procedure may involve reducing the size of a nose, removing a dorsal hump, and refining the tip the of the nose, Asian rhinoplasty and nose job surgery will often necessitate the addition of structural elements to the nose to add projection while also increasing the definition of the nose. In a standard rhinoplasty, often excess cartilage, bone and soft tissue may be removed to achieve the desired shape, with enough cartilage present in the septum to provide material for any grafts that may be necessary. In Asian rhinoplasty, typically the skin is thick relative to the strength of the intrinsic septal and nasal cartilage, and thus additional tissue (in the form of ear cartilage or rib cartilage) will be necessary to provide the requisite support to reshape the nose and skin envelope in a permanent fashion.
Which country is best for rhinoplasty Asian?
The best country of Asian rhinoplasty is the country that has the best rhinoplasty surgeon for you. Asian rhinoplasty is not a one-size fits all operation, and the selection of the best surgeon for you will come down to your aesthetic and functional goals and how they align with the training, background and expertise of your surgeon. Seoul, South Korea and Beverly Hills, California, United States are two of the most preeminent destinations for Asian rhinoplasty.
How long is recovery from Asian rhinoplasty?
After Asian rhinoplasty patients will have a cast on the bridge of their nose, and sutures will remain in place for a week. Even when additional grafts are taken from the ear, rib or fascia, all the surgical sites including the nose will heal simultaneously with the sutures being removed after the first week. At 2 weeks after surgery, most patients will feel ready to return to public, although the nose will be swollen. Much of the swelling will dissipate over the first 3-6 months, though it will take 1-2 years for full healing.
Where is the safest place to get a nose job?
The United States is known for having some of the highest standards in healthcare and cosmetic plastic surgery. The United States enjoys the privilege of having the very best universities and medical schools in the entire world, and ability to select only the best and brightest students to become medical doctors and surgeons equipped with the most comprehensive education and rigorous training. The US offers exceptional patient care and superlative plastic surgery and rhinoplasty outcomes, drawing patients domestic and international.
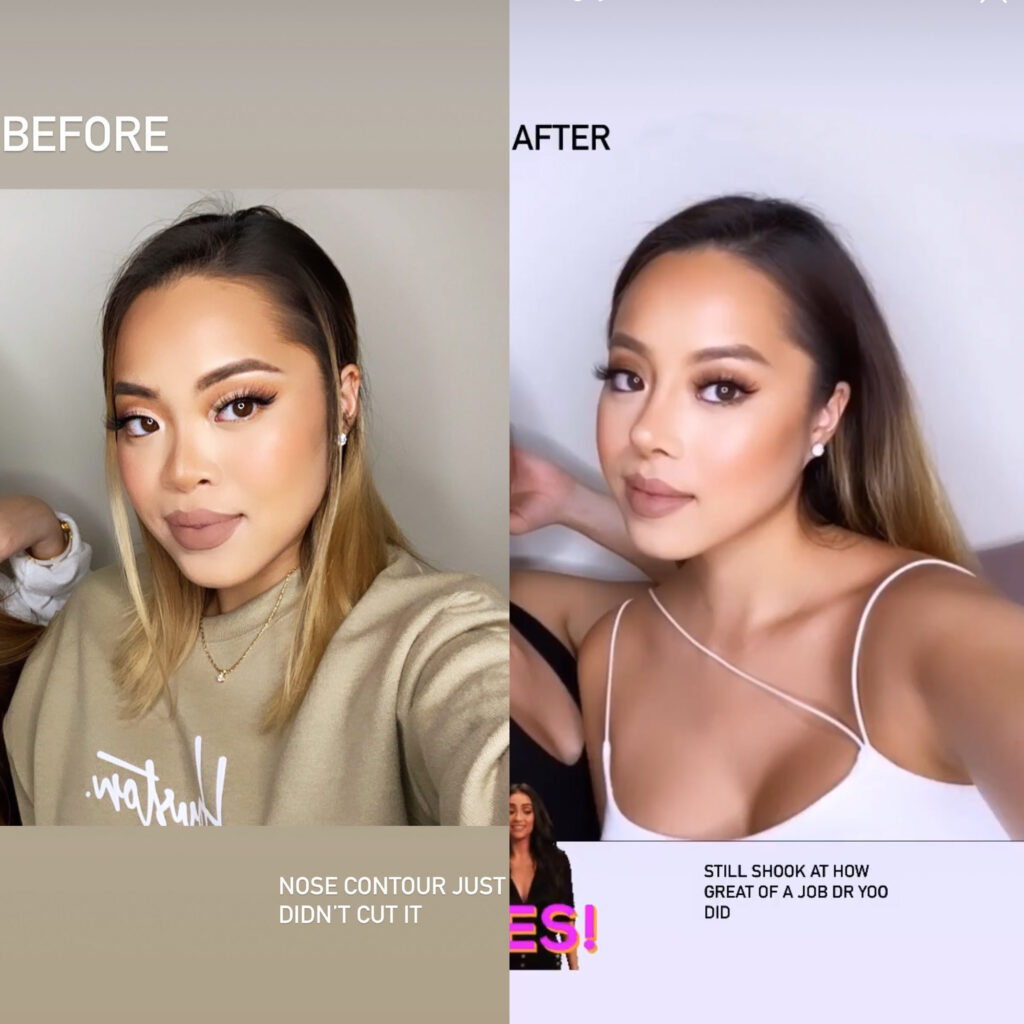
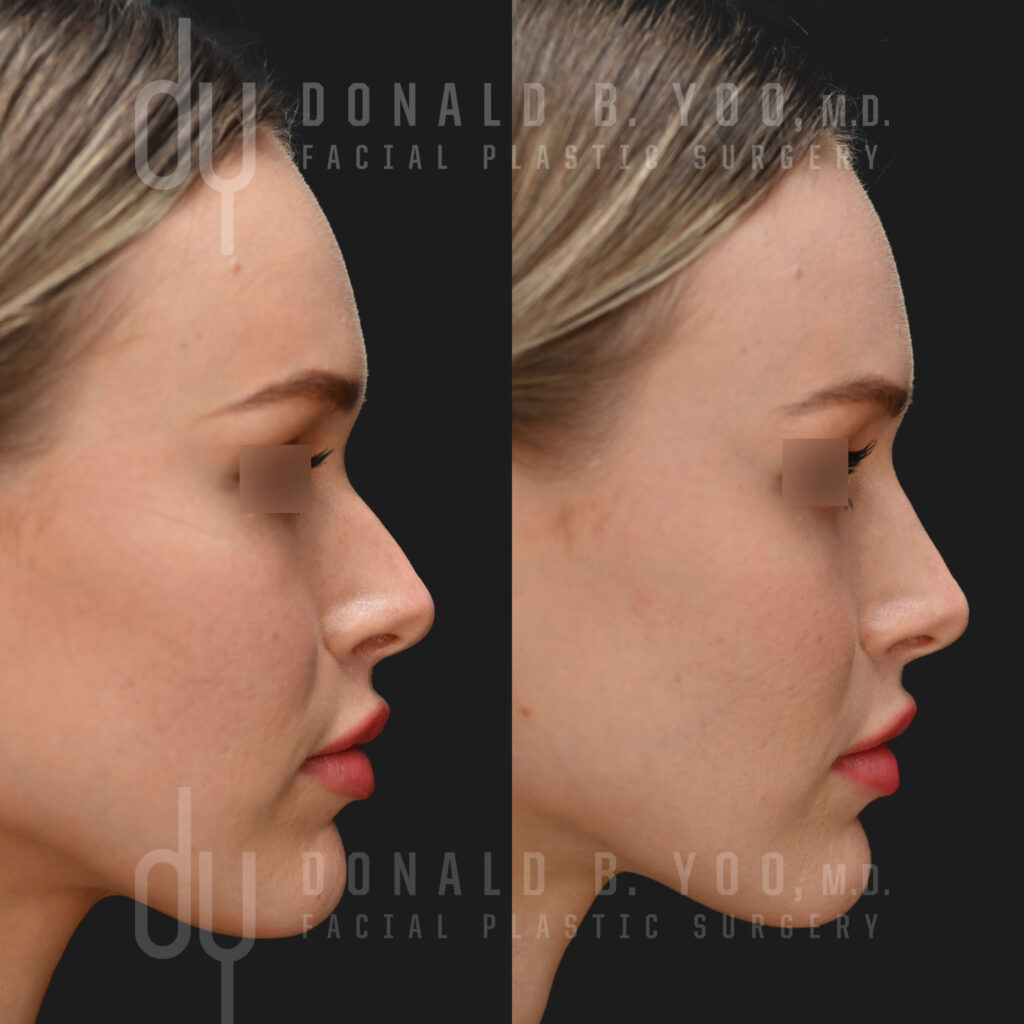
Before and after nose job without surgery with rhinoplasty specialist Dr. Donald B. Yoo, M.D.
Rhinoplasty without surgery, or non-surgical nose job, is a commonly performed procedure to reshape the nose in a temporary fashion. Using hyaluronic acid fillers, such as Restylane or Juvederm Voluma, the nose can be augmented and refined by adding volume to the nose in specific areas. Though the change is not permanent, and is limited compared to what is possible through surgical rhinoplasty and nose job, it does offer a way for patients to experience subtle to moderate changes, especially to the bridge or dorsum of the nose, with more subtle changes to the tip projection and tip aesthetics.
Duration: How long does nonsurgical rhinoplasty last?
Depending on the type of hyaluronic acid filler, a nonsurgical nose job will typically last between 9-18 months. The body will naturally absorb the filler material during this time until the nose returns to its pre-procedure state.
Process: How is nonsurgical rhinoplasty performed?
The skin of the nose will be numbed with a topical anesthetic, which typically takes 20-30 minutes. After the skin has been anesthetized and the nose has been aseptically prepped, the nonsurgical nose job is performed by multiple transcutaneous injections using a hyaluronic acid filler to add volume to specific areas of the nose. Most injections will be injected directly above the periosteum of the bone, or deep in the subcutaneous fat underneath the skin, and when performed expertly can improve nasal contours, symmetry, add augmentation, increase projection, rotate or counter-rotate the nasal tip, and increase definition and refinement of the nose in a safe manner.
How successful is non-surgical rhinoplasty?
In the hands of an experienced rhinoplasty surgeon, skilled in non-surgical rhinoplasty, the results will almost always be successful as long as the surgeon and patient have had a realistic discussion of the expectations and limitations of the procedure. Proper candidates for nonsurgical rhinoplasty will have nasal shapes than can be improved with the addition of volume, not the reduction of volume.
Is it possible to fix your nose without surgery?
The shape of the nose can be changed and improved nonsurgically with hyaluronic acid fillers in a procedure called nonsurgical rhinoplasty or nonsurgical nose job. The dermal filler material can add volume to the nose to improve aspects including contour, symmetry, and projection. The degree of correction is limited compared to surgical rhinoplasty, and the results are temporary, but can in many cases provide a significant improvement with minimal downtime.
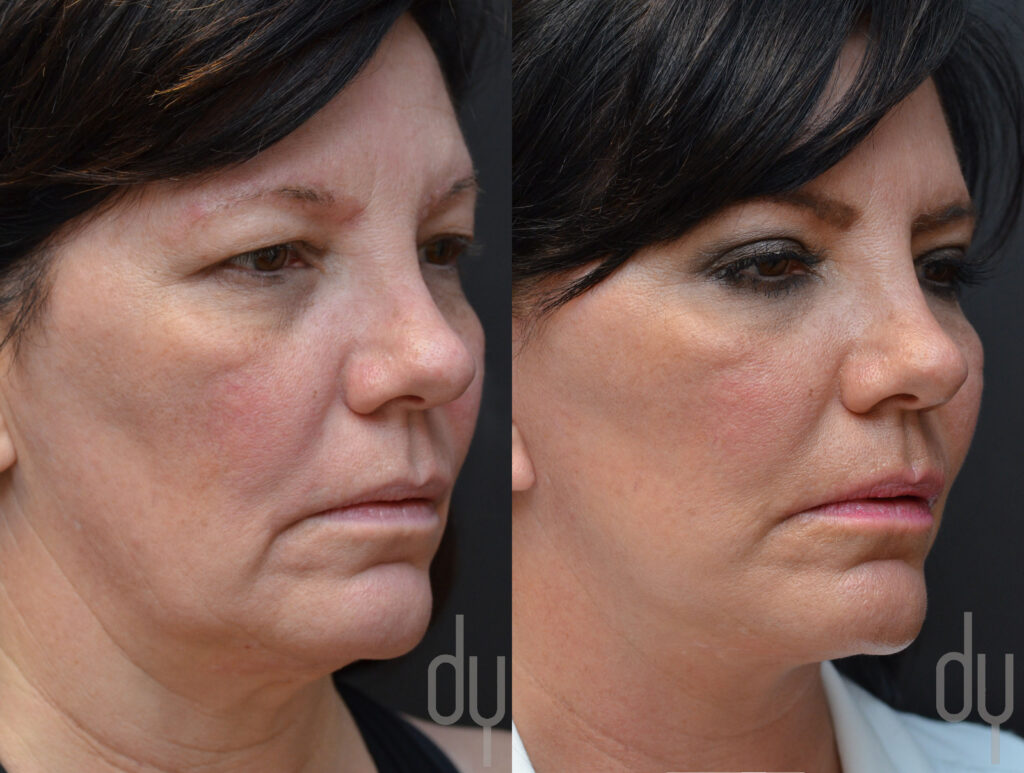
Facelift, or rhytidectomy, is a common facial plastic surgery procedure performed to address the signs of aging by repositioning ptotic and sagging tissue, removing excess skin and facial fat, while restoring volume to deficient areas. The overall effect is a more youthful appearance to the midface and cheeks, jawline and neck.
How long does a facelift last?
A facelift reverses many of the signs of aging to the mid-face, lower-face, jowls, jawline and neck, but does not stop the process of aging. It can be thought of as reducing one’s appearance by ~10-15 years. Patients who are very proactive about addressing the signs of aging will plan for two facelifts in their lifetime.
What is the best age to have a facelift?
A well-performed facelift can reasonably be expected to last for 10-15 years. With this timeline, the most typical age to undergo a facelift is 45-50, though this will vary based on individual factors such as genetics, lifestyle and cumulative sun exposure. Patients with unusually lax skin and early signs of facial aging may even consider a facelift as early as 35.
Is a facelift very painful?
Facelift surgery and rhytidectomy is not typically painful, as much of the face and neck is actually somewhat numb immediately after the procedure, due to the dissection required to mobilize the skin and soft tissue in the face and neck. Range of motion of the neck is slightly limited in the short term, and may feel tight, leading to a sensation of tenderness. Most patients will experience only minor discomfort after a few days or recovery.
How much does a facelift cost?
The cost of a facelift will depend on the skill and experience of your surgeon, as well as your individual anatomy and specific aesthetic goals.
What types of facelifts are there?
While many variations of facelift and rhytidectomy techniques exist, most contemporary surgeons will favor an approach that incorporates a deep-plane dissection as its foundation, while incorporating specific techniques to best address the neck, mid-face and periorbital areas that will suit the individual patient’s aesthetic goals and the patient’s unique anatomy.
Lip augmentation is typically performed as a non-surgical, office-based procedure with a hyaluronic acid filler. Hyaluronic acid fillers have revolutionized aesthetic medicine and plastic surgery since first being FDA approved in 2003 for their strong safety profile, ease of use, and predictable results.
Lip augmentation with facial fillers typically last between 6-12 months, depending on the type of hyaluronic acid filler used. The ideal filler for the lip is soft and silky, allowing the natural qualites of the lips to be preserved. Two of the most popular fillers for lip augmentation are Restylane Kysse and Juvederm Volbella, as they both are able to give a hydrated and full appearance to the lips, while retaining a completely natural aesthetic.
What is in lip fillers?
Hyaluronic acid gel fillers such as Restylane Kysse and Juvederm Volbella are synthetic versions of the glycosaminoglycans that are present in skin naturally, providing volume and elasticity. With aging, and loss of hyaluronic acid, skin becomes thinner, less elastic and more prone to wrinkling and forming rhytids. Hyaluronic acid gels are synthesized in a manner that causes them to last longer than naturally occuring HAs, but will still be absorbed normally by the body over time.
How long does lip filler last?
Lip fillers and lip augmentation with facial fillers will typically last 6-12 months, depending on the type of filler used. Hyaluronic acid fillers such as Restylane Kysse and Juvederm Volbella are the safest and most predictable way to add volume and hydration to the lips.
Which is better lip filler or lip augmentation?
In the past, surgeons have tried to augment the lips in a number of creative, and ultimately abandoned, ways. The difficulty with surgical augmentation is that the lips are an anatomically delicate area that has complex movement, abundant nerve endings, and central to one’s appearance. The ideal augmentation will move naturally, feel soft and silky like natural lips, and be precise to place. For all the advances of modern medicine, at the moment the best material for this is hyaluronic acid filler.

















 Contact Us